What AI Really Does in Hospitals Today — and Where It Still Fails
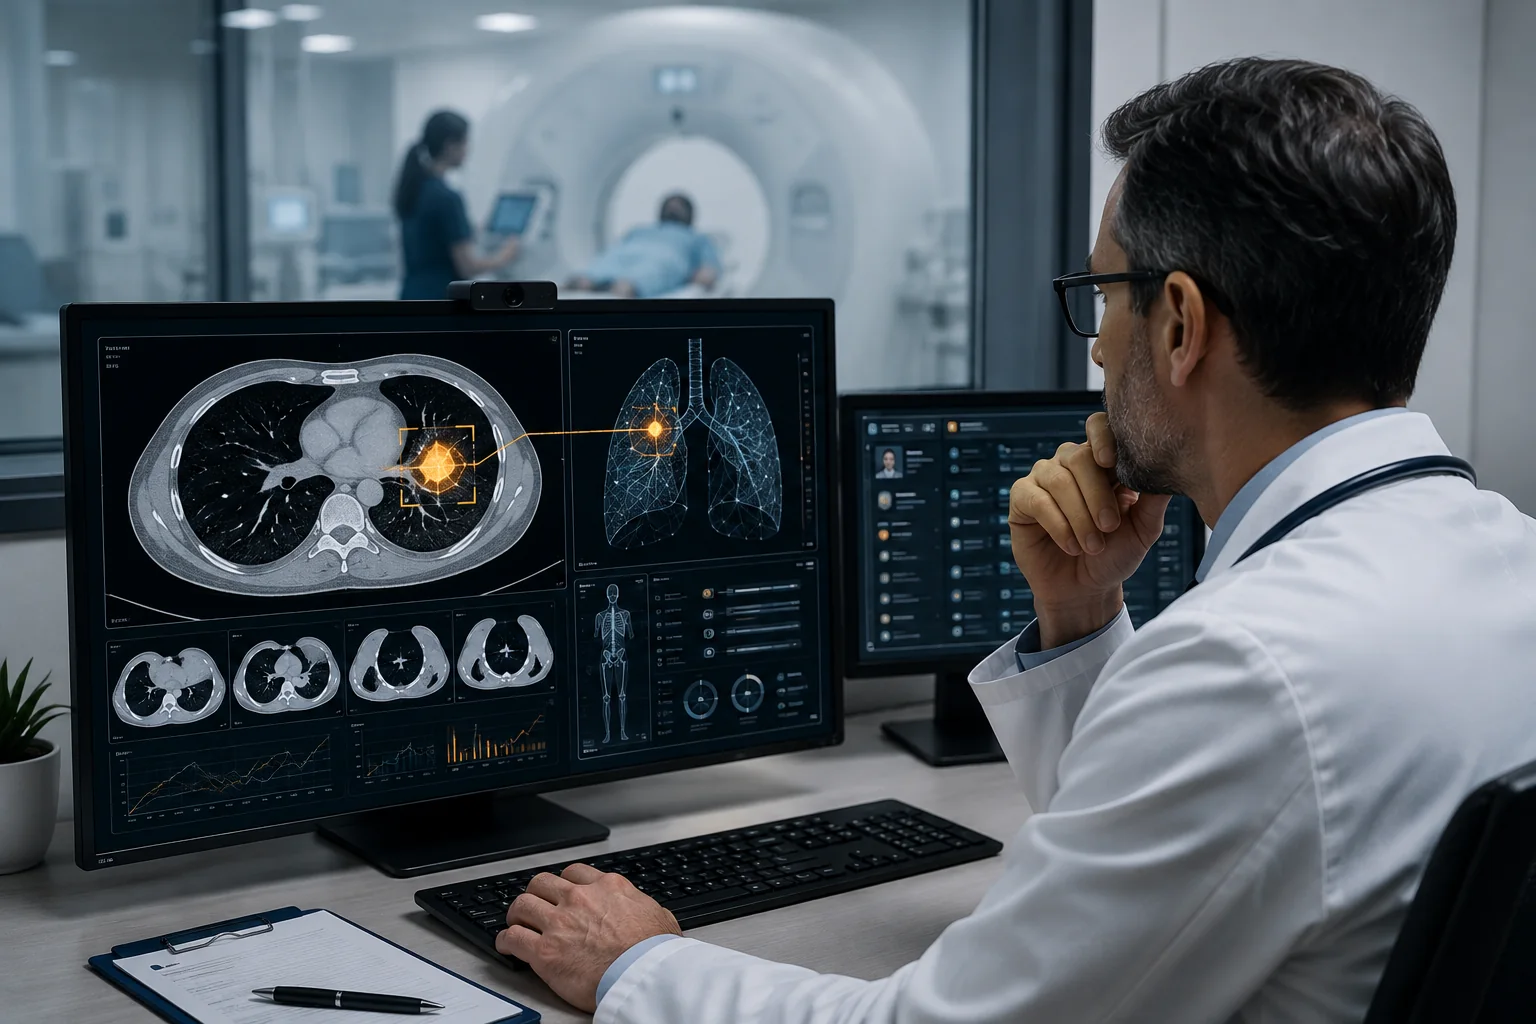
AI in Healthcare is transforming modern hospitals faster than ever before. From AI-assisted diagnosis to predictive analytics and clinical decision support, artificial intelligence is helping hospitals improve efficiency, detect diseases earlier, and enhance patient care. Yet despite these advances, doctors remain at the center of every critical medical decision.
Watch the Companion Video
This article accompanies the documentary The Hospital That Doesn’t Need Doctors?, examining how AI is used across modern medicine — with the studies, numbers, and failures behind the technology.
The real question is not whether AI will replace doctors. It is whether it can hand them the right information at the exact moment a life depends on it.
A Hospital Drowning in Data
Imagine the world’s best specialists examining the same patient at once — without any of them entering the room. That is roughly the promise made for artificial intelligence in medicine, and it lands at a moment when hospitals need it. For centuries care has been reactive: a patient notices symptoms, sees a physician, gets tested, receives a diagnosis, and begins treatment. That model saved millions of lives. But it now runs into a problem earlier generations never faced — modern medicine is drowning in data.
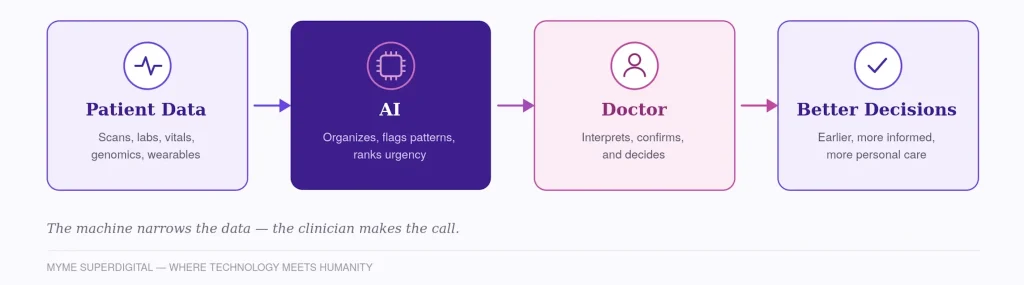
The scale is substantial: a single intensive-care patient can generate a continuous stream of physiological measurements, alongside electronic records, laboratory results, medical imaging, medications, clinical notes, and data from bedside monitors. Across a hospital, these streams quickly accumulate into an enormous volume of information. The challenge is not simply collecting data, but identifying the signals that may require timely clinical attention. In critical care, delays in recognizing important changes can have serious consequences. AI can help not by replacing a physician’s judgment, but by processing large volumes of data and helping clinicians organize, prioritize, and flag potentially important information as it arrives.
| KEY TAKEAWAYS – AI is helping hospitals move from purely reactive care toward earlier detection and prediction, in part by helping clinicians process and prioritize large volumes of medical data. – Some of the strongest evidence comes from medical imaging. In large prospective studies, AI-supported screening has increased cancer detection without increasing overall recall rates. – In biomedical research, AlphaFold has predicted structures for more than 200 million proteins. The work behind AlphaFold was recognized with part of the 2024 Nobel Prize in Chemistry, and its primary value is accelerating foundational research rather than producing finished drugs. – AI is not autonomous clinical judgment. Documented limitations and failures—including IBM Watson for Oncology and evaluations of the Epic Sepsis Model—illustrate the importance of rigorous validation, appropriate deployment, and human oversight. – The more realistic near-term model is an AI-augmented hospital: machines can help process data and identify patterns, while clinicians remain responsible for interpretation, judgment, and patient care. |
The AI Decision Loop in Healthcare
From Waiting Rooms to Continuous Care
Traditional care begins when a patient decides they need it. AI-supported care can begin earlier. Wearables, home monitors, and biometric sensors stream heart rate, oxygen, sleep, and activity into health systems continuously. On their own, a slight rise in resting heart rate or a small dip in oxygen may mean nothing; together, they can signal that something is already changing inside the body — and when that is caught early, hospitals gain the one thing medicine has always been short of: time.
That time is operational as well as clinical. With advance notice of incoming critical cases, administrators can ready intensive-care beds, adjust staffing, and clear supply bottlenecks before demand hits crisis levels — the hospital beginning to behave less like a queue and more like a system that anticipates its own load. The patient journey, in this model, no longer starts in the waiting room. It starts wherever the patient happens to be.
Teaching Machines to See What Humans Might Miss
Medical imaging is where the evidence is strongest. Radiologists train for years to spot subtle abnormalities in scans; deep-learning systems, trained on millions of prior images, add a tireless second pair of eyes that reads every image with the same consistency at 9 a.m. or 9 p.m. The results are now measured in large, prospective studies, not just demos.
In Germany’s PRAIM study, published in 2025, 463,094 women were screened for breast cancer by 119 radiologists. Radiologists using AI support detected about 17% more cancers (6.7 versus 5.7 per 1,000 women) than those working without it, without increasing the overall recall rate. Related research is also examining whether AI-supported screening can help identify cancers that might otherwise emerge between scheduled screenings.
The critical detail is how that gain was achieved: AI worked with radiologists, not instead of them. When researchers tested letting AI read low-risk scans autonomously, the approach did not clearly meet the safety bar of expert double-reading. In oncology especially, where an early catch can transform survival, AI is best understood as an assistant that highlights suspicious regions for a human to confirm — the final diagnosis stays with the physician.
| MYME INSIGHT The headline is not “AI beats doctors.” It is “doctors plus AI beat doctors alone.” Nearly every credible result in medical AI is a story of augmentation — the human and the model each covering the other’s blind spots. At its best, AI closes the gap between what medicine collectively knows and what any single clinician can realistically hold in mind and process at the bedside. |
Precision Medicine Instead of Trial and Error
Medicine has long relied on treatments developed from evidence across groups of patients. But two people with the same diagnosis can respond differently to the same treatment, influenced by factors such as genetics, medical history, environment, and other individual characteristics. AI can help analyze complex combinations of clinical, biological, and genomic data to identify patterns that may inform more personalized treatment decisions. This does not replace clinical judgment; it can broaden the evidence available to clinicians and help them interpret information that would be difficult to assess manually at scale. The decision—and the responsibility—still belong to the clinician.
AI in the Operating Room
When treatment means surgery, technology can shift from analysis to physical assistance. Robotic surgical systems already allow surgeons to operate with precise instrument control, using features such as motion scaling and tremor reduction. AI is increasingly being explored as an additional layer for tasks such as image analysis, surgical guidance, and decision support. In these systems, the surgeon remains responsible for the procedure—this is technology augmenting human skill, not replacing it with autonomy.
Some of the biggest gains can happen before the first incision. Patient-specific three-dimensional models built from medical imaging can support surgical planning by helping clinicians visualize anatomy and evaluate different approaches before an operation. More advanced digital-twin concepts aim to extend this idea by creating dynamic computational representations of individual patients that could support simulation and prediction. The goal is not to automate the operation but to give surgical teams better information for planning and decision-making. These technologies remain tools for augmenting surgical expertise, not substitutes for the surgeon.
Accelerating Drug Discovery
Developing a medicine has long been among the slowest, costliest processes in science — years of screening millions of compounds before a single candidate reaches the lab, then more years of trials. AI is compressing the earliest stage. The landmark is AlphaFold, the system from Google DeepMind that predicts a protein’s three-dimensional shape from its amino-acid sequence — a 50-year grand challenge in biology. It has now predicted the structures of roughly 200 million proteins, nearly all known to science, and made them freely available; in 2024 its creators, Demis Hassabis and John Jumper, shared the Nobel Prize in Chemistry.
It is important to be precise about what this does. Knowing a protein’s shape reveals where a drug molecule might bind — the first step in designing a medicine, not the last. Every candidate still faces laboratory validation, clinical trials, and regulatory review, and AI-discovered drugs are only beginning to enter those trials. What AI changes is the starting point: instead of searching millions of possibilities almost blindly, scientists begin with a far shorter list of promising ones. The result is not instant medicine — it is a faster, better-aimed beginning.
The Real Division of Labor
Strip away the science-fiction framing and a clear pattern emerges across every one of these areas — a division of labor, not a takeover:
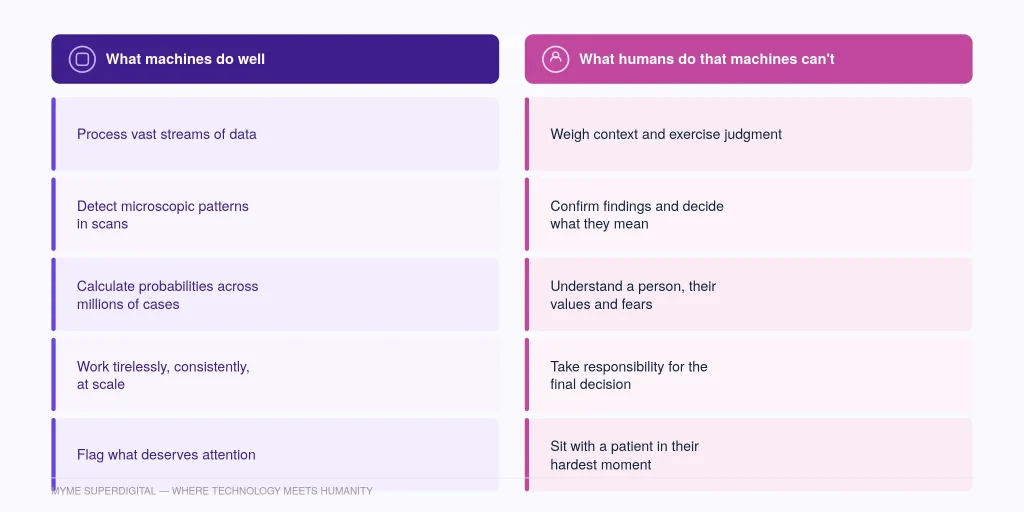
The realistic model of AI medicine: machines handle the heavy lifting so clinicians can do what only humans can.
What Can Go Wrong
The same power that makes medical AI useful also makes its failures dangerous — and there are real ones, not hypothetical ones, worth naming plainly.
When the model is wrong
IBM’s Watson for Oncology, once marketed as a revolution in cancer care, was found by a 2018 STAT investigation — citing internal documents — to have produced multiple examples of “unsafe and incorrect” treatment recommendations. In one training case, it suggested a drug carrying an explicit warning against use in patients with severe bleeding for exactly such a patient. The cause was mundane and instructive: it had been trained on a small number of hypothetical cases rather than robust real-world data. The product was eventually wound down.
The Epic Sepsis Model, one of the most widely deployed early-warning tools in U.S. hospitals, offers the second lesson. When University of Michigan researchers independently validated it (JAMA Internal Medicine, 2021), it missed roughly two-thirds of sepsis cases while generating enough false alerts to risk “alert fatigue.” Impressive performance on the vendor’s own data did not survive contact with a different hospital’s reality — a textbook case of why external validation is non-negotiable.
Bias and privacy
AI learns from historical data, so if that data underrepresents certain groups, accuracy can vary by demographic — quietly widening health inequalities instead of narrowing them. And these systems run on some of the most sensitive data ever assembled: records, images, genomes, continuous biometrics. As hospitals interconnect, cybersecurity becomes as critical as clinical excellence, and a single breach can compromise privacy or disrupt care. None of this is an argument against the technology. It is an argument for diverse training data, transparent evaluation, strong security, and continuous human oversight — fairness and safety have to be built deliberately, not assumed.
| MEDICAL DISCLAIMER This article is general information, not medical advice. AI tools described here are used by clinicians as decision support; diagnosis and treatment remain the responsibility of qualified healthcare professionals. For any personal health concern, consult a licensed clinician. |
| MYME INSIGHT The wrong question is whether AI will replace physicians. The real shift is that AI removes the invisible barriers — the searching, the documentation, the data overload — that keep doctors from practicing at their best. Machines process data; doctors provide judgment. Machines recognize patterns; doctors understand people. |
Frequently Asked Questions
Will AI replace doctors?
No. Today’s healthcare AI is designed to assist clinicians — analyzing data, flagging patterns, and supporting decisions. Diagnosis, treatment planning, and care remain the responsibility of qualified professionals, and the strongest evidence shows doctors working with AI outperform either alone.
Where does AI help most in medicine today?
Medical imaging (especially cancer screening), clinical decision support, precision medicine, robotic-assisted surgery, remote monitoring, hospital logistics, and early-stage drug discovery are among the most developed applications.
Are AI diagnoses always accurate?
No. AI can improve efficiency and catch patterns humans miss, but it also makes errors — sometimes serious ones, as the Watson and Epic sepsis cases show. Clinical validation and physician oversight are essential, and a model that performs well in one hospital may fail in another.
Is the fully autonomous hospital coming?
The evidence points to AI-augmented hospitals, not autonomous ones. The most effective systems combine machine intelligence with human expertise rather than removing clinicians from the loop.
MyMe SuperDigital Perspective
It may help to think of AI the way we think of electricity in medicine. Electricity did not replace doctors; it transformed what they could do — powering the imaging, monitors, and operating theaters modern care is built on. AI is shaping up to be another piece of infrastructure like that. Its greatest contribution is unlikely to be any single algorithm or robot. It will be a hospital where information moves instantly, risks are seen earlier, treatments are tailored more tightly, and clinicians spend more time with patients than with screens.
The hospital that “doesn’t need doctors” is unlikely to exist. The hospital that lets doctors practice medicine more effectively — freed to listen, to explain, and to decide — is one we can already start to build. That is the version worth aiming for: not intelligence that replaces the human at the bedside, but intelligence that finally gives them back the time to be there.
Continue Exploring This Topic
- The Future of Healthcare: Can AI Smart Bands Really Save Your Life?
- Digital Immortality: Can AI Really Outlive You?
- Can Artificial Intelligence Help You Grow? The Truth About AI Coaching
- The AI Education Paradox: Why Schools Must Rethink Learning
References
Clinical Research
Eisemann, N., Bunk, S., Mukama, T., et al. (2025). Nationwide real-world implementation of AI for cancer detection in population-based mammography screening (PRAIM). Nature Medicine, 31, 917–924. doi.org/10.1038/s41591-024-03408-6
Lång, K., et al. (2023). Artificial intelligence-supported screen reading versus standard double reading in the mammography screening with AI trial (MASAI). The Lancet Oncology. doi.org/10.1016/S1470-2045(23)00298-X
Habib, A. R., Lin, A. L., & Grant, R. W. (2021). The Epic Sepsis Model Falls Short — The Importance of External Validation. JAMA Internal Medicine, 181(8), 1040–1041. doi.org/10.1001/jamainternmed.2021.3333
Jumper, J., et al. (2021). Highly accurate protein structure prediction with AlphaFold. Nature, 596, 583–589. doi.org/10.1038/s41586-021-03819-2
Topol, E. J. (2019). High-performance medicine: the convergence of human and artificial intelligence. Nature Medicine, 25, 44–56.
Reporting & Background
Ross, C., & Swetlitz, I. (2018). IBM’s Watson supercomputer recommended ‘unsafe and incorrect’ cancer treatments. STAT News. statnews.com
The Royal Swedish Academy of Sciences (2024). The Nobel Prize in Chemistry 2024 (AlphaFold; Hassabis, Jumper, Baker). nobelprize.org
